This is default featured slide 1 title

Go to Blogger edit html and find these sentences.Now replace these sentences with your own descriptions.

This is default featured slide 2 title

Go to Blogger edit html and find these sentences.Now replace these sentences with your own descriptions.

This is default featured slide 3 title

Go to Blogger edit html and find these sentences.Now replace these sentences with your own descriptions.

This is default featured slide 4 title

Go to Blogger edit html and find these sentences.Now replace these sentences with your own descriptions.

This is default featured slide 5 title

Go to Blogger edit html and find these sentences.Now replace these sentences with your own descriptions.

Tuesday, August 9, 2005

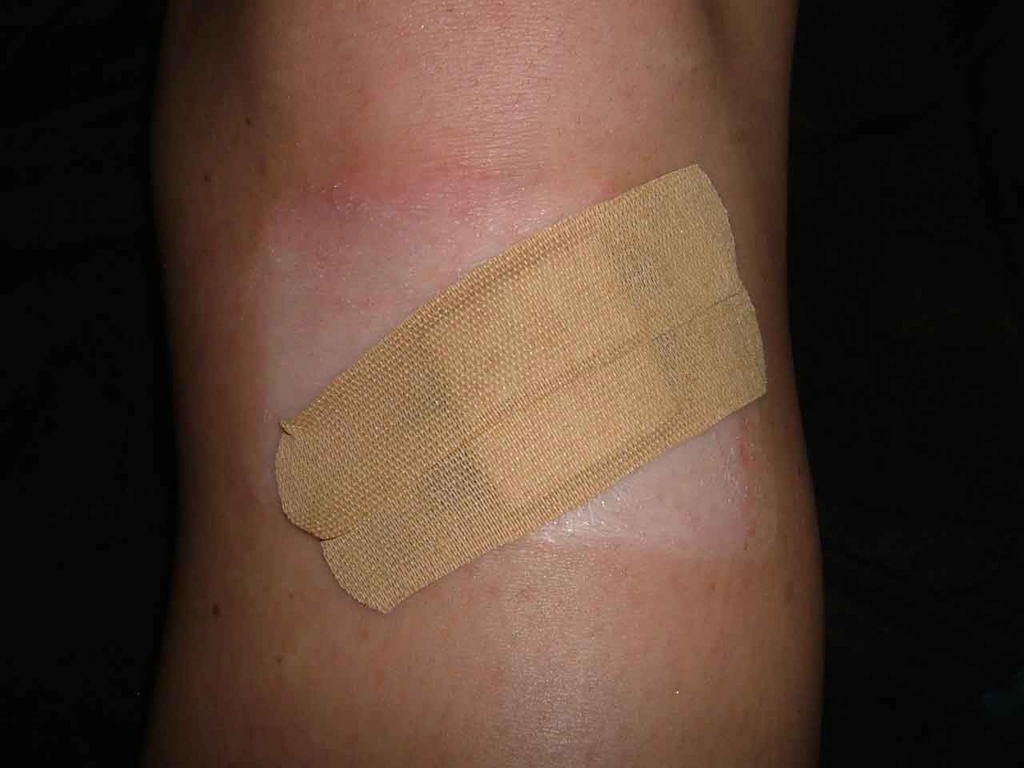
Nevus, Congenital


This 20 yo college student presented in consultation for removal of a congenital nevus.
The lesion is located just distal to her left knee. She's been embarrassed about this since childhood and for the past six or seven years won't let anyone see it. Indeed she covers it at all times with bandaids.
The lesion measures 5.2 cm in diameter.
I have referred her to a surgeon for removal since I think that's better than psychotherapy. To minimize the scar it may need staged excision.
The young woman appears normal in all other respects - she is very upset about the lesion and the questions she gets about it.
I wonder if this has been reported. I would hardly call this Body Dysmprphic Syndrome.
Your thoughts are appreciatged.

Not much written about this area -- here's a ref that may touch on it:


Congenital melanocytic nevi. Evaluation and management.
Marghoob AA., Dermatol Clin. 2002 Oct;20(4):607-16, viii.
Department of Medicine, Dermatology Division, Memorial Sloan-Kettering Cancer Center, 1275 York Avenue, New York, NY 10021, USA. marghooa@mskcc.org

This article discusses the care of patients with CMN, who often require
a multidisciplinary approach involving pediatricians, family physicians,
internists, dermatologists, psychologists, plastic surgeons,
neurologists, and radiologists. The cosmetic and psychosocial issues,
combined with the knowledge of the increased risk of developing
melanoma or NCM, is a huge burden that many of these patients
and their families have to carry. This article describes the importance
for physicians to help these patients and families come to terms
with these issues, as well as remind their patients and their family
members that although melanoma, NCM, or other complications can
develop, most affected individuals do not develop any complications.
The article mentions that there are many healthy, happy, functional
adults with large, small, and multiple CMN alive today.

Monday, August 8, 2005

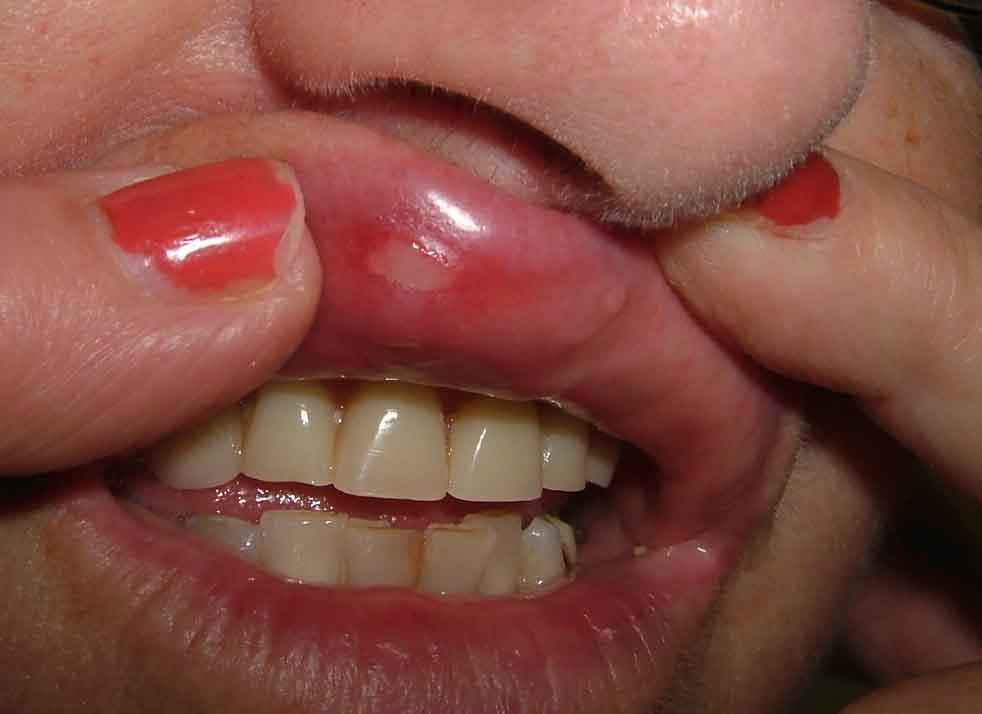
Imiquimod Side-Effect?


This 66 yo woman began topical imiquimod on July 27, 2005 for a biopsy proven superficial BCC of the right upper lip. One week later, she developed aphthous ulcers on the mucous membrane surface of the area just below the site treated. A literature search retrieved a reference to his occurence. This is another unexpected adverse effect. It is unclear how common this is.

Aphthous ulcers associated with imiquimod and the treatment of
actinic cheilitis.
Chakrabarty AK, Mraz S, Geisse JK, Anderson NJ.
J Am Acad Dermatol. 2005 Feb;52(2 Suppl 1):35-7.
Solano Clinical Research, Davis, California, USA. chakak3@yahoo.com

Our case series report is the first documented depiction of the
appearance of aphthous ulcers secondary to imiquimod
application. This case series presentation discusses the
underlying pathophysiology of aphthous ulcer development and
imiquimod therapy in terms of the stimulation of pro-
inflammatory cytokines, such as tumor necrosis factor alpha
(TNF-alpha). The literature review suggests more than just a
mere coincidence for the development of aphthous ulcers
subsequent to the treatment of actinic cheilitis with imiquimod
application.

Sunday, August 7, 2005

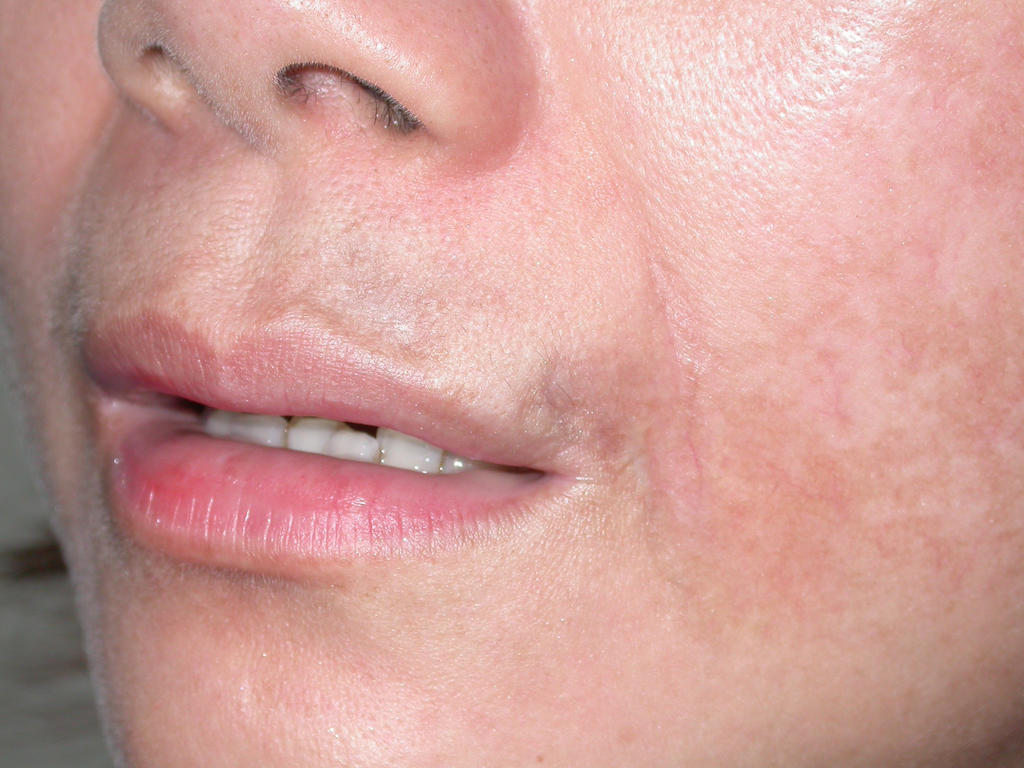
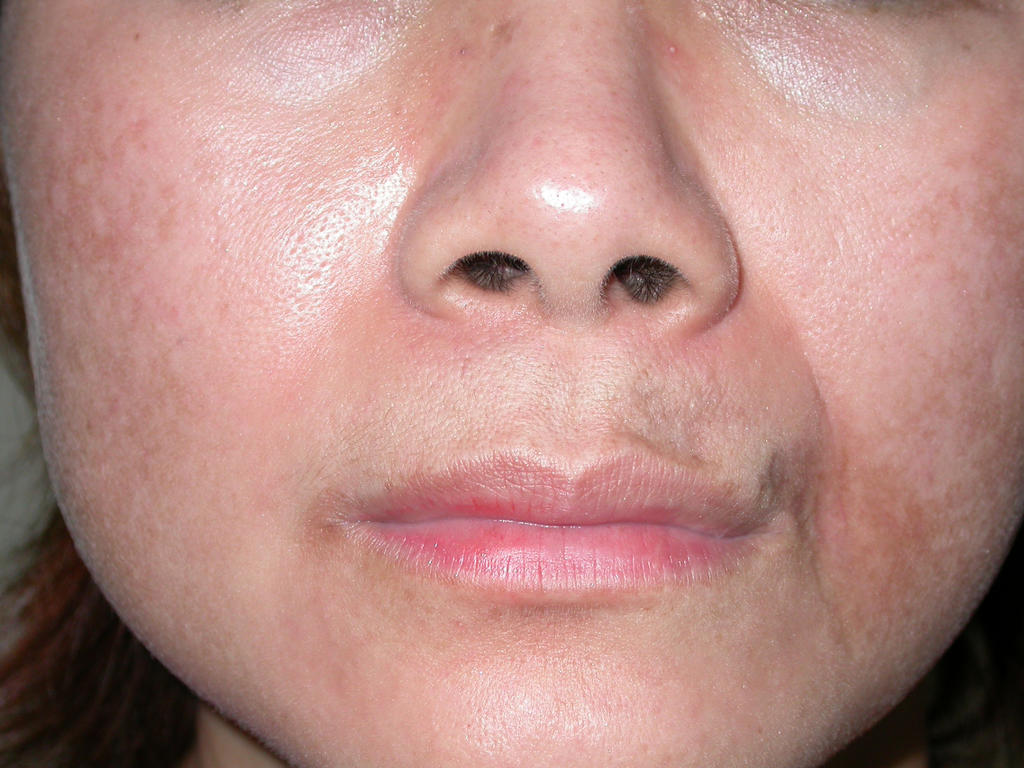
46 year old woman with indurated depressed lesion


A 46-year-old woman presented with 7 years history of depressed lesion just above the left side of mouth. It was asymptomatic. She has seen few dermatologists and a plastic surgeon but none really helped her lesion. She did not have polyarthalgia or other constitutional symptoms. Drug history was nil significance.
Examination showed 2 areas of depression, almost tethered to the underlying dermis just above the left side of the mouth and another a bit above the angle of mouth. There is no induration on deep palpation. The inner buccal mucosa appeared normal.
Serology for lupus including ANA, anti Ro, Anti La, and other extractable nuclear antigens were negative. Possible diagnoses would include lupus profundus and morphoea. Biopsy with immunofluorescence studies should help. Anyone has any therapeutic pearls for this lady??

Basal Carcinoma - Deconstructed

August 9, 2006.

LATE BREAKING!! BIOPSY HERE SHOWED THE LESION TO BE AN INTRADERMAL NEVUS.
I should have paid more attention to the history.

MORE... The patient underwent an excision - and the final report was a Basal Cell + an intradermal nevus. Quite unusual. The initial clinical impression was more accurate that the incisional biopsy. This is sobering.


This 57 yo man presented with an 8 mm in diameter papule that has bled since he started to wear glasses a year or so ago. He has been aware of a slowly growing lesion in this area since age 19 (38 years ago).
The lesion has been biopsied and I await the results. It appears to be a BCC. The long history underscores the benign behavior of many of these lesions. While we have all seen case reports of aggressive BCCs that have caused loss of eyes, ears, nose - these are likely in the very small minority. It is the growth characteristics and behavior of these lesions which is likely key, not their appearance micorscopically. Our therapy for these indolent tumors may be too aggressive based on the slow growth and lack of metastatic potential.

Thursday, July 28, 2005

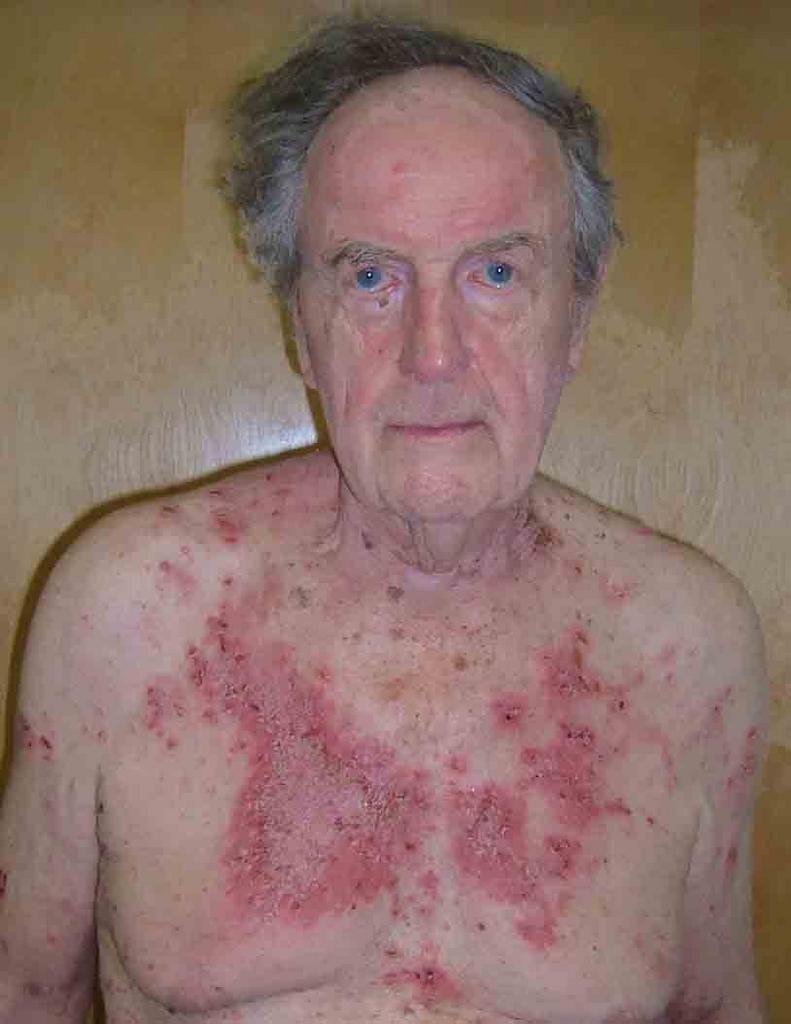
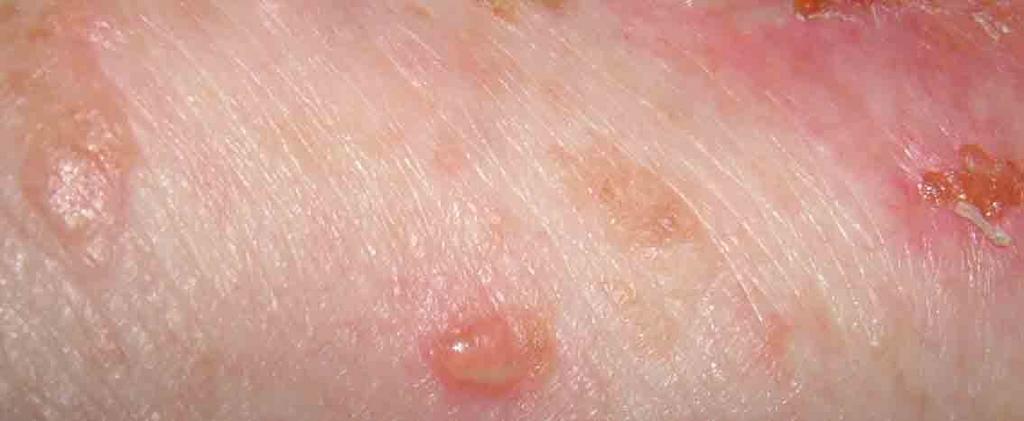
84 yo man with Pemphigus


This 84 yo man was seen around weeks ago with an erosive bullous process on torso, head and neck of 4 months duration. He was on no meds by mouth and in good general health.
My initial impression was pemphigus vulgaris vs. impetigo. The skin culture showed many coag + staph, and the bx showed an acantholytic bulla. The DIF was positive for intracellular IgG.
He was treated with dicloxacillin 250 mg qid and prednisone 20 mg tid.
He cleared quickly. At present he is on 30 mg per day of prednisone and tapering by 5 mg every two weeks. He's had no new lesions since therapy was initiated and his itch has disappeared.
Questions:
1) Value of adjuvent therapy? I am thinking of starting in a benign manner with minocycline/
2) Should I try to get on alt. day steroid first?
3) Any suggestions?
Follow-up (August 6, 2005) The patient continues to do well. He is now on Prednisone 20 mg per day. No symptoms and no new lesions. His prednisoe will be dropped by 5 mq every 10 days until 10 mg per day - then we will convert to alt day therapy. I may add minocycline 100 mg bid.

40 yo woman with scarring alopecia


The patient is a 40 yo woman with an eight year history of scarring alopecia.
Her ANA is + at 1:160 - all other labs are normal.
No other cutaneous findings or systemic disease other than "fibromyualgia."
She has been treated with 200 mg of plaquenil b.i.d. for a number of years. This has not been of much help.
The patient is quite concerned about her scalp. She's going through a divorce and worries about her appearance.
Questions?
1) Any value to a biopsy?
2) Would scalp reduction be an option?
3) Role for hari transplantation? Should a biopsy be done first

Tuesday, July 12, 2005

Melanonychia in a Six Year-Old Child

Presented by
Dr. Chee Meng Loh
RMG
Singapore
E mail: bliss88@singnet.com.sg

The patient is a six year old Chinese girl who developed a dark pigmented longitudinal band on the nail of her right index finger about 1 year ago. It started as a narrow, light brown band and grew in darkness (black in centre of band, and lighter shade of brown at edge of band) and width. The band is now about 3 mm in width. It has not changed in the past 3 months.

There is no history of trauma to the right index finger. There is also no complaint of pain in that finger.

The girl suffers from eczema and is on steriod medication (hydrocortisone 1% cream). She is otherwise healthy. There is no history of melanoma in the girl, her parents or grand parents. Neither her parents have pigmented bands on their nails.

Physical Exam: Dark longitudinal pigmented band on right index finger.
Colour ranges from black to brown.
Width is about 3 mm.
(Pictures attached)

Biopsy not performed.

Diagnosis: Melanonychia of right index finger.

Questions:
What are the likely causes of melanonychia in this child?
What is the likelihood that the cause is melanoma?
Should biopsy be performed to rule out melanoma?
If yes, what biopsy procedure is appropriate and what is the risk of permanent damage to the nail?
If a wait and see approach is appropriate, what other signs should the parents watch out for and within what time frame?


Melanonychia
Originally uploaded by David Elpern.


Melanonychia
Originally uploaded by David Elpern.