This is default featured slide 1 title

Go to Blogger edit html and find these sentences.Now replace these sentences with your own descriptions.

This is default featured slide 2 title

Go to Blogger edit html and find these sentences.Now replace these sentences with your own descriptions.

This is default featured slide 3 title

Go to Blogger edit html and find these sentences.Now replace these sentences with your own descriptions.

This is default featured slide 4 title

Go to Blogger edit html and find these sentences.Now replace these sentences with your own descriptions.

This is default featured slide 5 title

Go to Blogger edit html and find these sentences.Now replace these sentences with your own descriptions.

Saturday, November 12, 2005

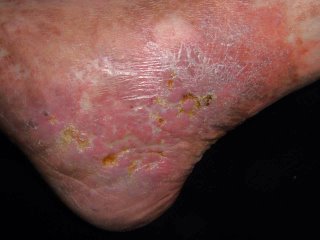
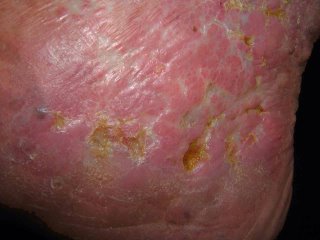
84 yo Man with Atrophie Blanche

The patient is an 84 yo man with a ten year history of extremely painful ulcerations of his lower legs.
Other than whirlpool baths, I have found nothing to be of value.
His health is good and he has bounding dorsalis pedis and posterial tibial pulses.
I assume this is Atrophie Blanche.
Do you have any therapeutic suggestoins?


Monday, October 31, 2005

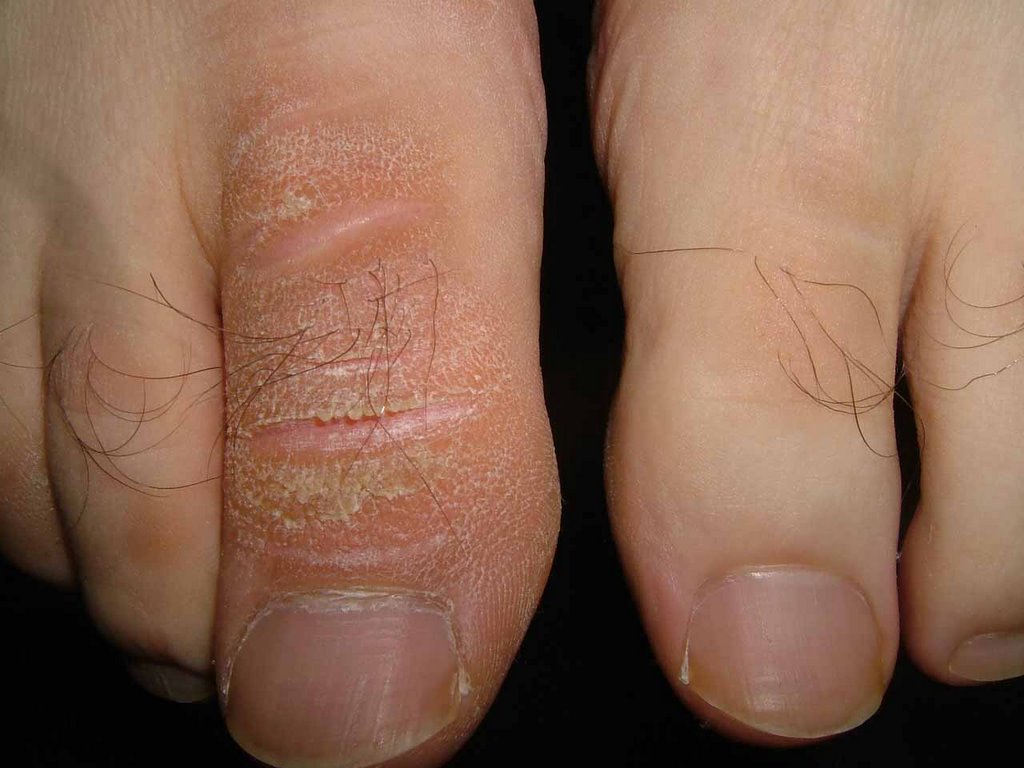
Localized Hyperkeratosis

39 yo man with > 15 year hx of localized hyperkeratosis of right great toe. No unusual trauma to area. He's used mostly over the counter emollients without much help.

Are you aware of any localized forms of hyperkeratosis?

I have started him on Salex cream.

Pictured below are his affected right and normal left great toes.

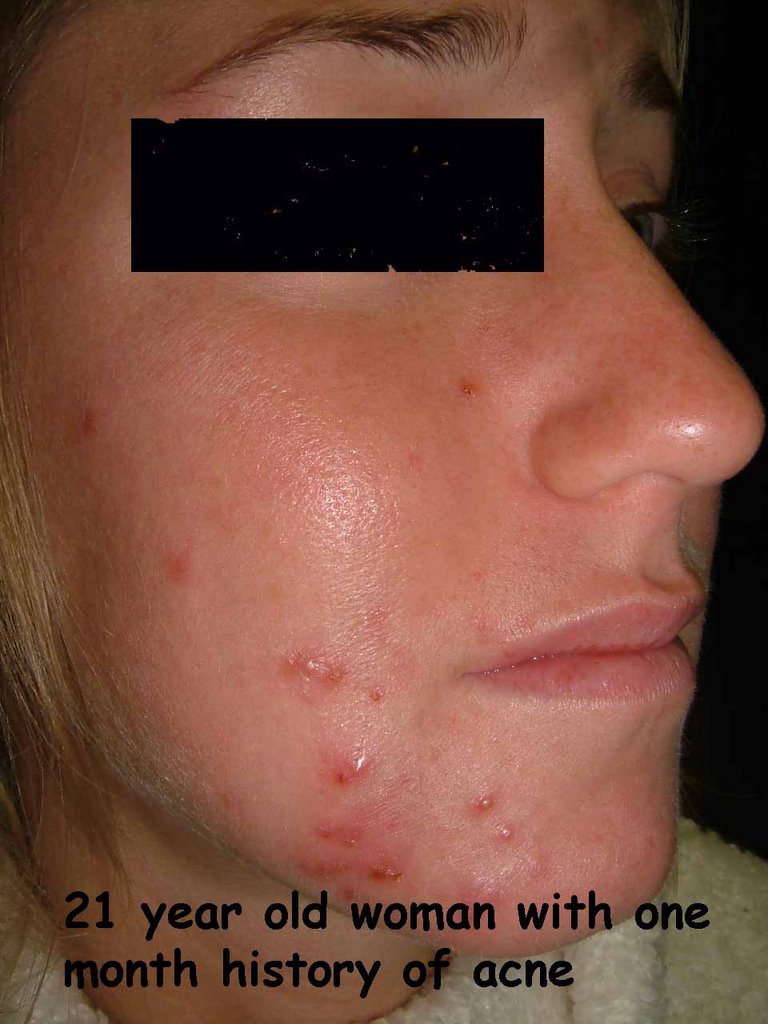
Recent Onset Acne in Young Woman


This 21 yo woman experienced the sudden onset of acne one month ago.
No new med. No unusual stresses.
She has never had acne like this before.

Do you think this is a mild case of pyoderma faciale rather than typical acne?

Sunday, October 30, 2005

BCC Scalp


The patient is a 75 yo man with a three month hisory of a lesion at the vertex of the scalp.
Exam: Man with Type II - III skin. 2 x 1.6 cm diameter erythematous plaque scalp. There are some small crusted areas.
Biopsy shows superficial BCC.

Question: Is Aldara appropriate?
C + E will take ages to heal.
Excision could n ot be closed without a graft or a flap.

Wednesday, October 26, 2005

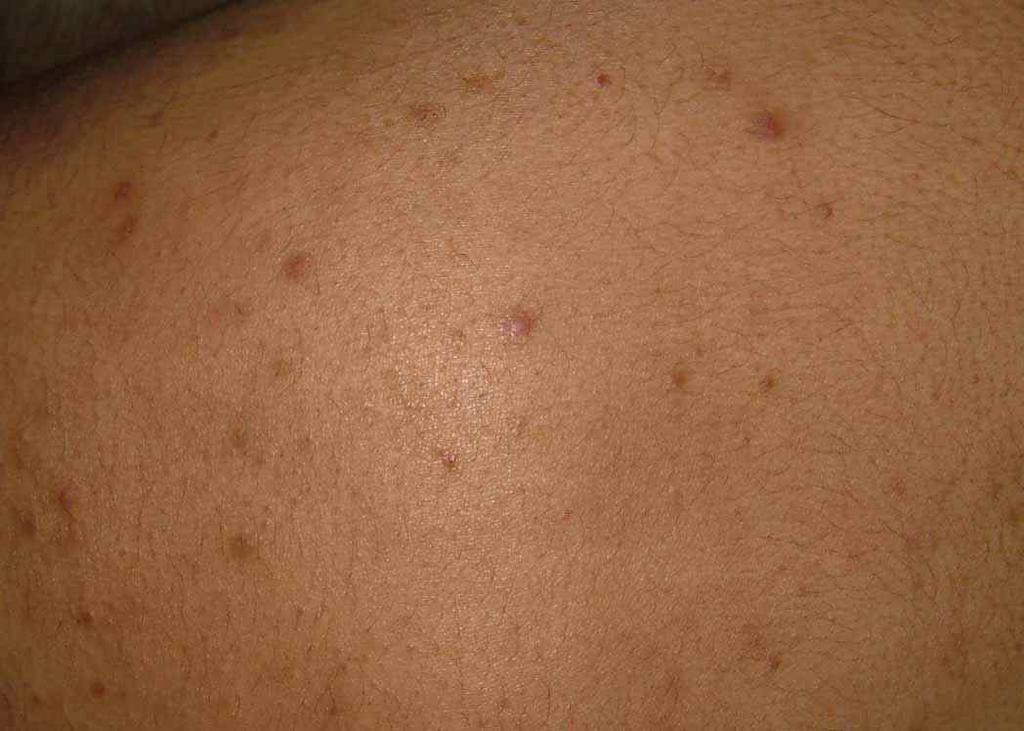
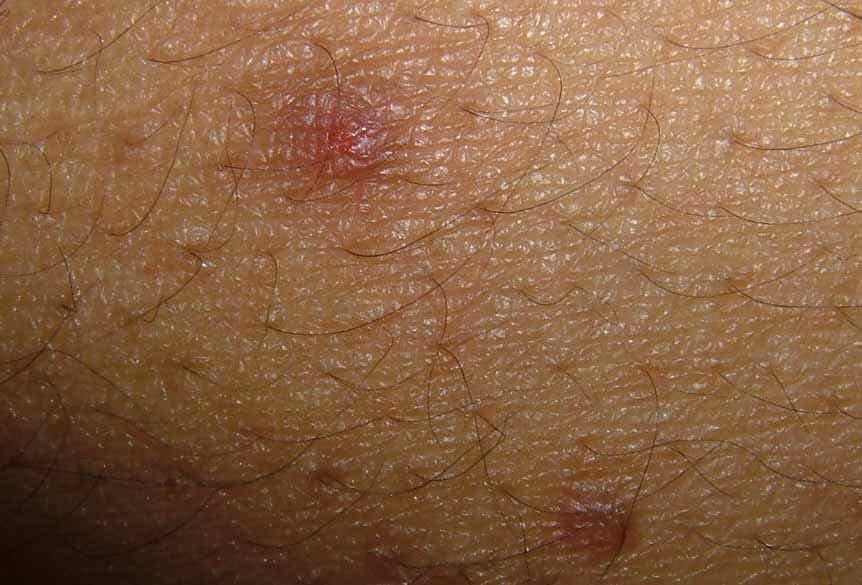
19 year old student with acneiform eruption


History: 19 year-old man with a 5 year history of acneiform eruption predominately on torso and proximal extremitiesl Some facial involvement, but less than on torso. He is in good health, no history of diabetes or steroid use. No antibiotics for months. In the past he has used benzoyl preoxide ceams and washes, topical retinoids, topical antibiotics and tetracycline and its derivatives. Mome has ever helped.

Exam: Healthy young man with Type IV skin. On torso and proximal extremities he has discrete erythematous papules and an occasional pustule. No cysts. Face largely clear.


Lab: nil

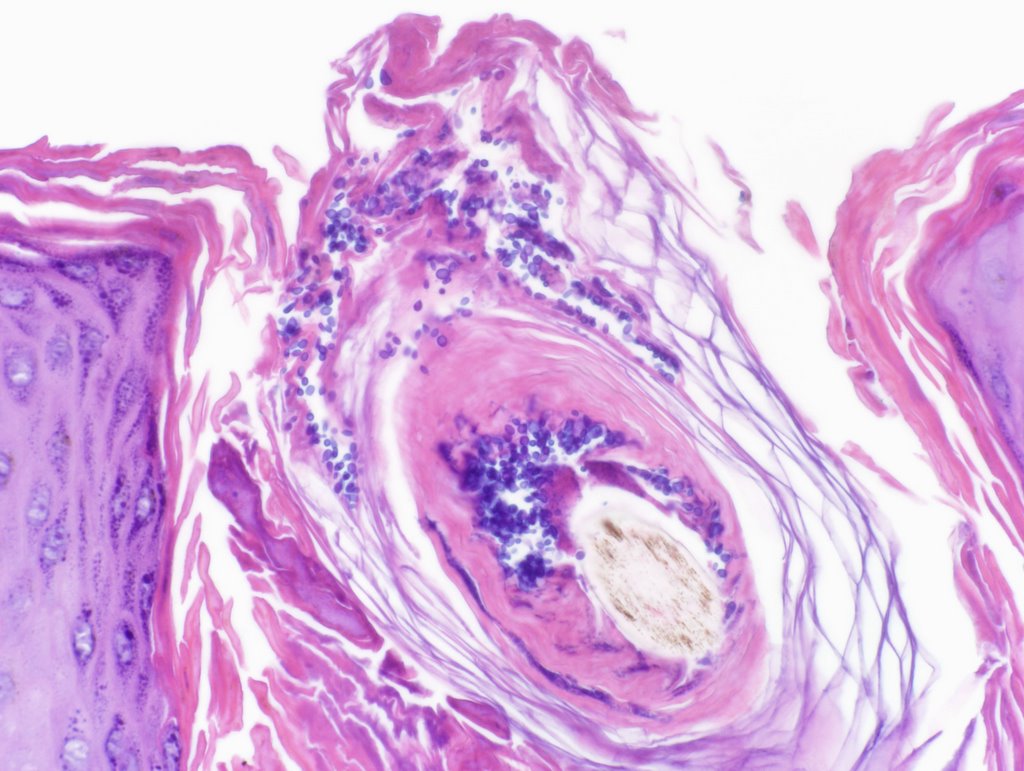
Pathology: Initial reading showed marked perifollicular lymphoneutrophilic infiltrate c/w acute folliculitis. PAS negative.


Diagnosis: Probable Pityrosporon folliculitis

Discussion: Are the yeasts incidental or indicative of pityrosporum folliculitis. I asked for more cuts and this showed numerous PAS (+)"fungal spores" in the follicular ostia.
I have started him on itraconazole 200 mg per day and Nizoral 2% shampoo to torso. The literature does not have good guidelins for how to treat this; but I suspect 4 - 6 weeks woth oral meds.
Please suggest diagnostic and therapeutic alternatives.

Thursday, October 20, 2005

Atypical Nail Pits


Case for Discussion:
This 40 year-old woman presented for evaluation of a nail dystrophy present for 2-3 months.
She has a history of Hashimoto's thyroiditis. About 9 months ago she developed vitiligo.
Her health is otherwise normal
Meds. Synthyroid and iron
Lab: Thyroid Perox AB 248 (Nl. 0 - 34 IU/ML)
ANA < 1:40

Physical Exam:
Vitiligenous patches left neck and left upper back
Around 4 finger nails show a distinctive pitting. The pits are fairly uniform and the affected nails are rough and lusterless. There are no cutansous lesions of psoriasis.

Discussion and Questikon:
The picture is atypical for psoriatic nail pits but that is not excluded.
I favor a relationship to the underlying autoimmunity that has caused the Hashimoto's and vitiligo.
The picture is similar to that seen with alopecia areata, but the patient has not has any alopecic patches.
Nail dystrophy has occasionally been described before the development of A. areata. And patients with Hashimoto's thyroiditis have a higher than expected incidence of alopecia areata.
We welcome your thoughts or suggestions.

Saturday, August 13, 2005

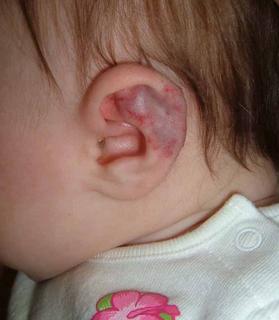
Hemangioma of Auricle


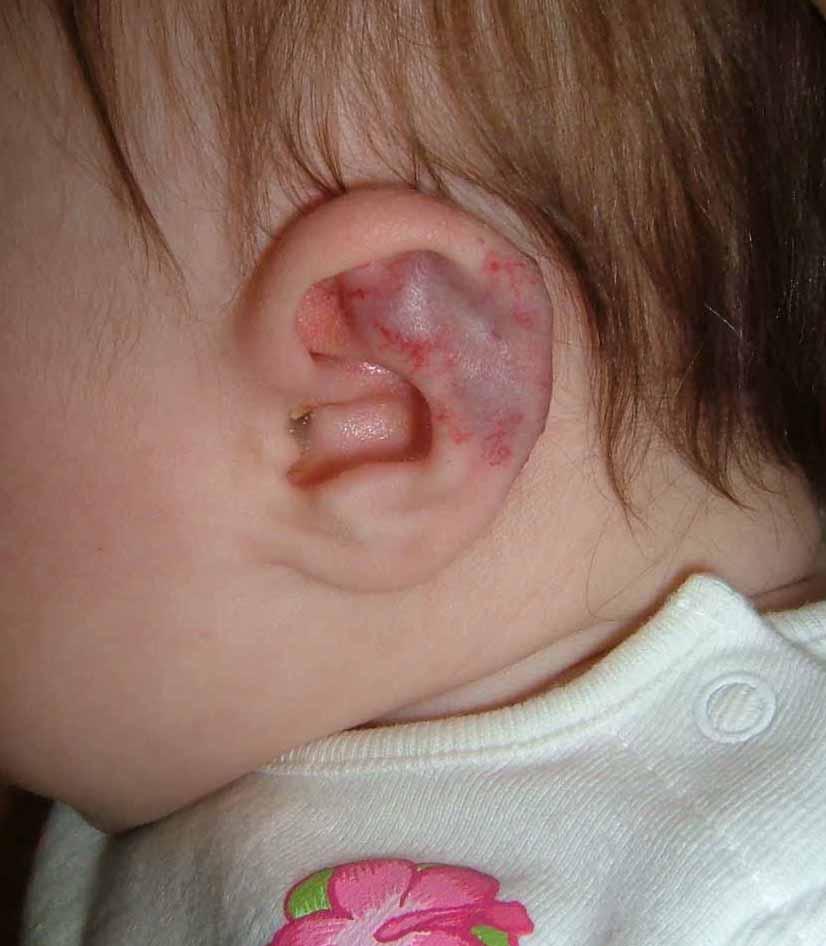
This 4 month infant girl was born with hemangiomas of the chin and left ear.
The lesion on the chin (not pictured) measures 1 cm in diameter and is typical of a congenital hemangioma.

The abnormality of the left ear involves the triangular fossa and the helix. I am concerned that as this involutes it could cause disfigurement. At the same time, I wonder if anyone has experience handling similar lesions in this site. A PubMed site found only a paucity of pertinent references.

Ref:
Cavernous hemangioma of the external ear canal.
Reeck JB, Yen TL, Szmit A, Cheung SW.
Laryngoscope. 2002 Oct;112(10):1750-2. Related Articles, Links
Division of Otology, Neurotology and Skull Base Surgery, Department of Otolaryngology-Head and Neck Surgery, Veterans Administration Medical Center, San Francisco, California, USA.

OBJECTIVE: To document the occurrence of a cavernous hemangioma of the external ear canal and to review the relevant literature.STUDY DESIGN Case report and literature review. METHODS: Review of a patient chart, imaging studies, operative report, and histologic findings. RESULTS: A cavernous hemangioma of the external ear canal not involving the tympanic membrane was surgically excised without complication. This is the third documented cavernous hemangioma of the external ear canal without tympanic membrane involvement in the English literature. Computed tomography scan is invaluable to narrow the differential diagnosis. Complete removal is curative. CONCLUSIONS: Cavernous hemangioma of the external ear canal with or without tympanic membrane involvement is a rare otologic entity amenable to surgical treatment. Temporal bone computed tomography scan imaging is an important preoperative diagnostic tool.