This is default featured slide 1 title

Go to Blogger edit html and find these sentences.Now replace these sentences with your own descriptions.

This is default featured slide 2 title

Go to Blogger edit html and find these sentences.Now replace these sentences with your own descriptions.

This is default featured slide 3 title

Go to Blogger edit html and find these sentences.Now replace these sentences with your own descriptions.

This is default featured slide 4 title

Go to Blogger edit html and find these sentences.Now replace these sentences with your own descriptions.

This is default featured slide 5 title

Go to Blogger edit html and find these sentences.Now replace these sentences with your own descriptions.

Wednesday, May 17, 2006

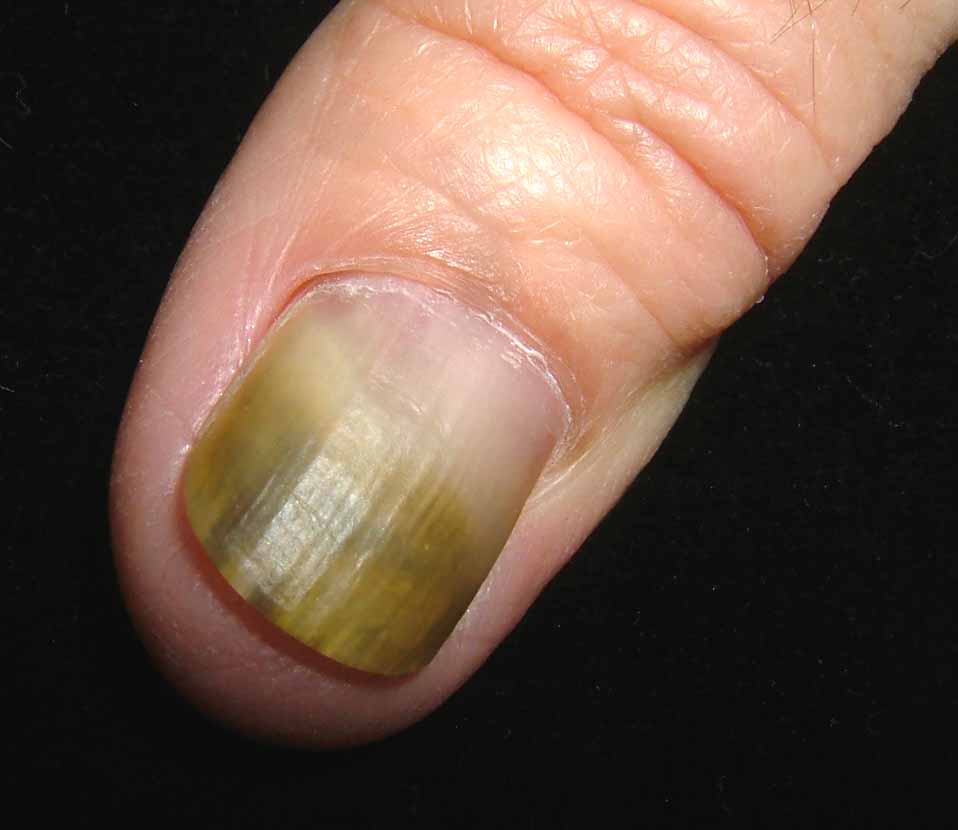
Onycholysis

The patient is a healthy 58 year old woman with a 3 year history of onycholysis. Fungal culture has grown out Candida zeylanoides. Bacterial culture negative.

Topicals have not been of help. (imidazoles and thymol in chloroform)
Would fluconazole be of value?
Should the nail be avulsed?
Who has had success treating this kind of problem?

Thursday, May 11, 2006

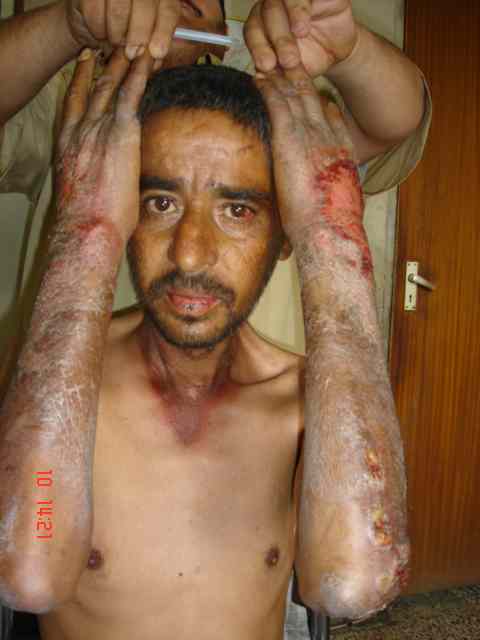
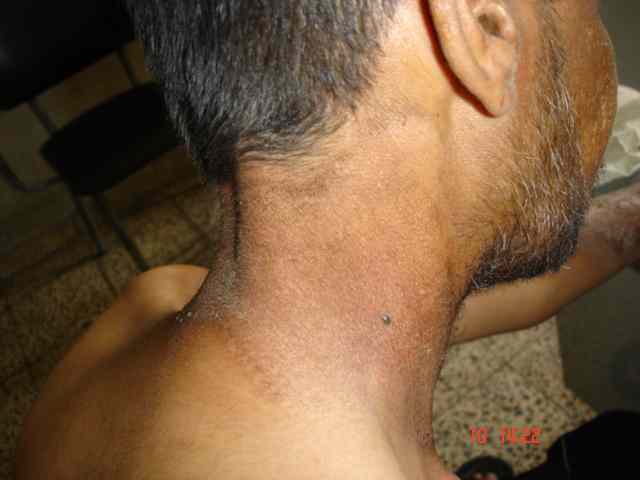
Pellagra in Alcoholics

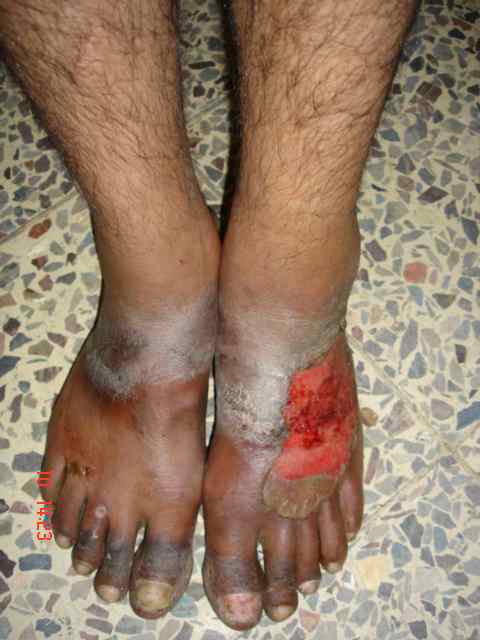
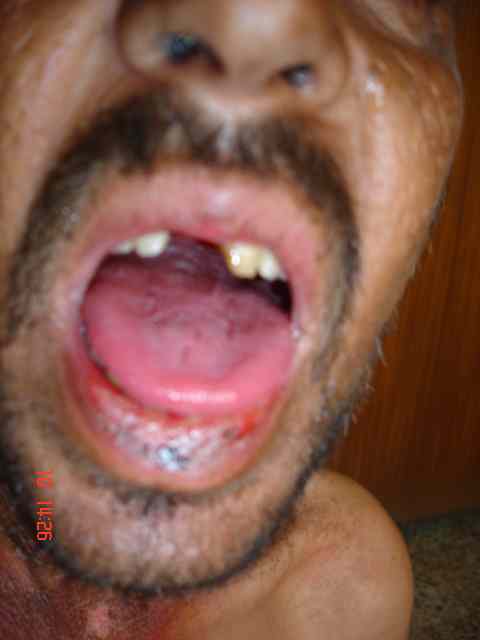
In Iraq, pellagra is only seen in sporadic cases in patients with alcoholism. I describe here a case of pellagra in 30 year old man who used to drink alcohol one litre a day of a local beverage called ARAK. In addition, his nutrition was poor. He developed a typical rash of pellagra in photosensitive area, some lesions are bullous together with beefy tongue. The rash resolved quickly after vitamin replacement but recurred when he resumed alcohol drinking.

I would like to ask my colleagues
1) how often see pellagra
2) what is the cause?


Monday, May 8, 2006

Nail Bed Carcinoma

The patient is s 70 yo man who was seen today for a three year follow-up of micrographic surgery for a sqaumous cell carcinoma of the nail bed. There is no evidence of recurrence and the results are cosmetically excellent.

I had another patient with a similar lesion. He was a VA patient and they did not approve him for microgrpahic surgery. He had the distal part of his thumb excised. Bizarre that health insurance trumps the interests of the patient.


Thursday, May 4, 2006

Folliculitis and Hair Loss

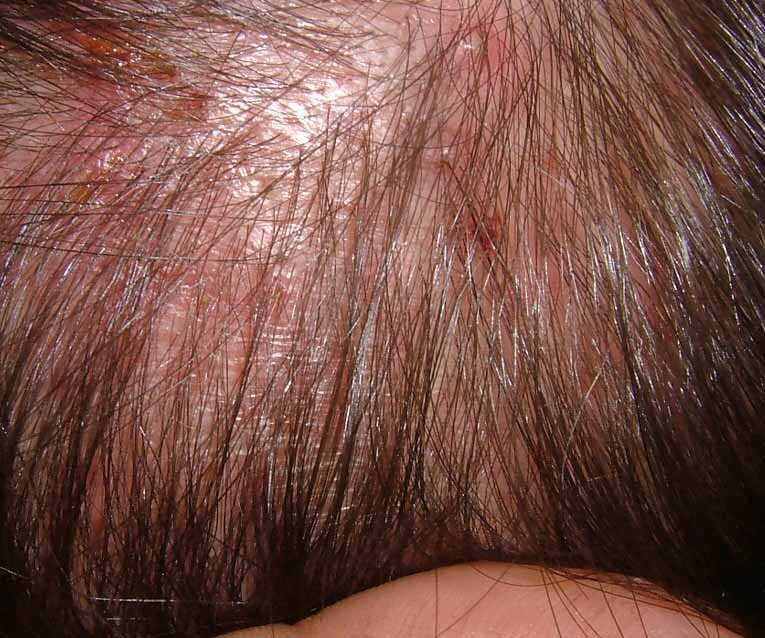
The patient is a 30 year-old man with a 2 year history of folliculitis and mild hair loss. He has erythematous papules and a few pustules scattered over the scalp. Cultures have been negative. Biopsy showed only inflammation c/w folloculitis. Minocycline has been of marginal help, but process recurrs when he stops. He has an occasional papule on his cheeks but no signs of rosacea. His hair is globally thin.

Question: Is this folliculitis decalvans? Would isotretinoin be worth trying? He is also interested in hair transplantation.


Friday, April 28, 2006

Volcanic Eruption

The patient is an 88 yo woman who came as a "walk-in" today.
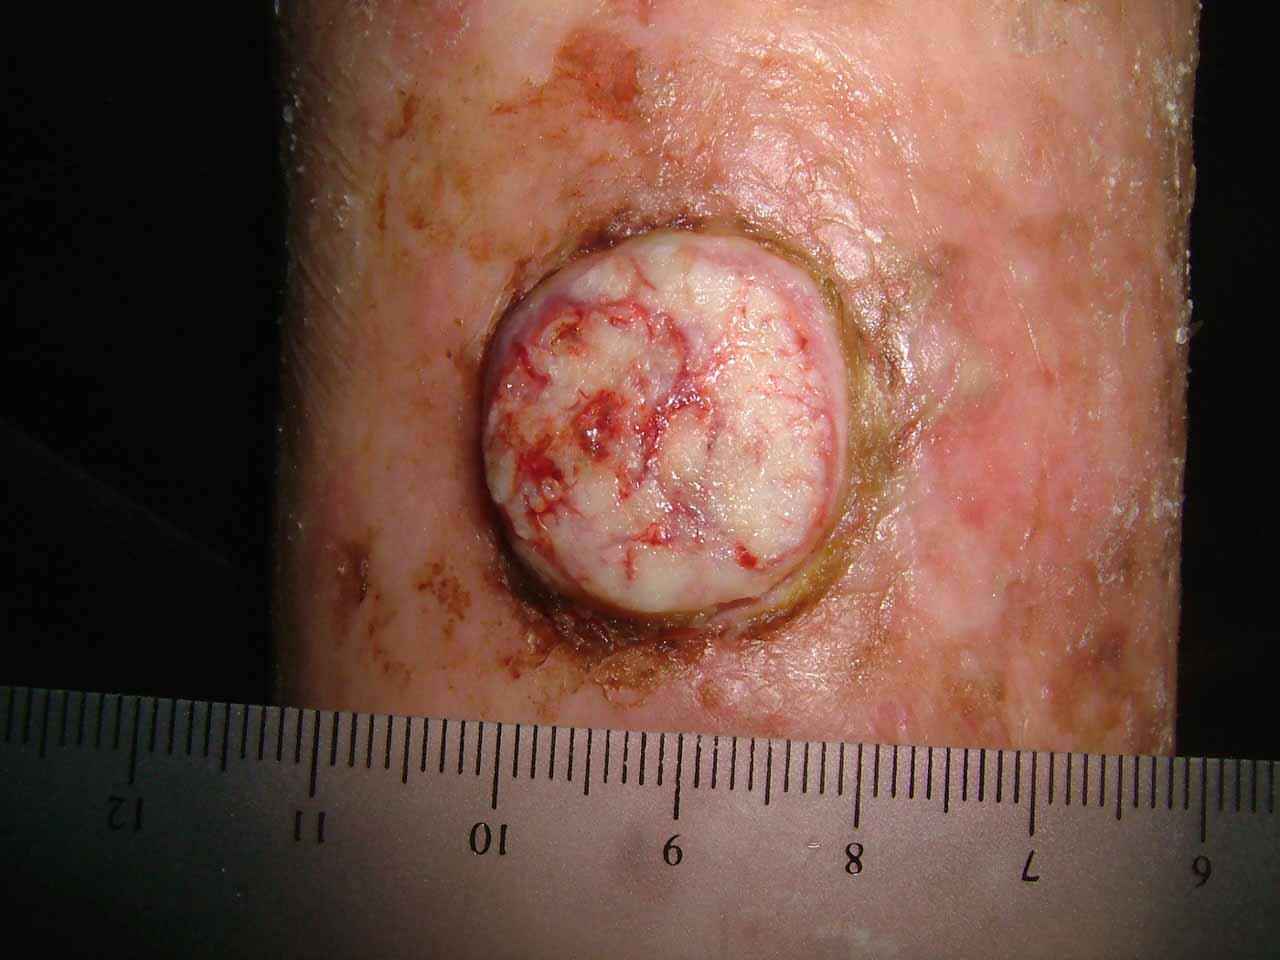
She said she had a "volcano erupt" on her leg two weeks ago.

The examination shows an alert actve 88 yo woman with Type II skin. She has a dome-shaped tumor on her right shin which measures 2.1 cm in diameter. It seems to have a collarette surrounding it. She has marked actinic damage.


The history suggests keratoacanthoma. Some dermatologists call this "Squamous Cell Carcinoma -- Keratoacanthoma type." I suspect this is a coding ploy to make them seem malignant.

My question is what to do?
1) It would be hard to close after excision in this site.
2) If it is curetted and dessicated, it make take weeks to months to heal.
3) It could be observed, however, some of these larger lesions can be locally agressive.
4) Intralesional methotrexate is a possibility.

My instinct is to treat with C and E, but I'd like some suggestions. I might follow that with Aldara. I am open to suggestions.

Thank you.

David Elpern

May 4, 2006
At the advice of a few of you, I did a shave biopsy and curetted and dessicated the lesion. The base was mostly gritty (a good sign). I will follow closely. She's 88 year-old. So, I'll observe before any further intervention. May try imiquimod. Will play by ear.

Saturday, April 22, 2006

Cream Complacency

A 60 yo man was seen yesterday for pruritic papules on scalp and extremities. He had seen another dermatologist over the years and had been treated with a host of topicals including liquid nitrogen. Biopsy showed Prurigo nodularis.
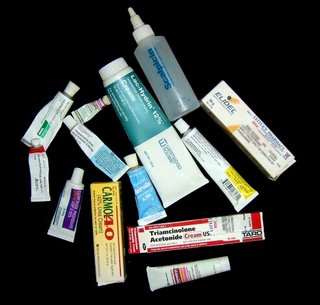

[Contents of Bag Brought in by Patient]


After a few years, he developed a febrile illness, was seen in the ER where a CBC showed a WBC of 80,000. He was eventually diagnosed with a rare T-cell lymphoma. Four courses of CHOP have put him in remission.

If his prurigo becomes more active again, one wonders if this will be a harbinger of recurrence.

Sobering lesson. Prurigo may be realated to an underlying malignancy. We can all be lulled into a cream complacency and miss an important clue. I can think of one or two patients over the years with unexplained excoriations who turned out to have a lymphoproliferative malignancy.

Reference:
Seeburger J, Anderson-Wilms N, Jacobs R.
Lennert's lymphoma presenting as prurigo nodularis.
Cutis. 1993 May;51(5):355-8.
Section of Dermatology, Loma Linda University School of Medicine, California.
Abstract:
Lennert's lymphoma is a peripheral T-cell lymphoma that only rarely involves the skin. We present the case of a forty-two-year-old man who experienced severe pruritus for ten months. He was repeatedly diagnosed as having neurodermatitis
and prurigo nodularis before subtle hematologic clues suggested, and subsequent examination of bone and lymph node biopsy specimens confirmed, the diagnosis of Lennert's lymphoma. This report describes the case and presents a brief review
of Lennert's lymphoma.

Friday, April 21, 2006

U.P in a Newborn


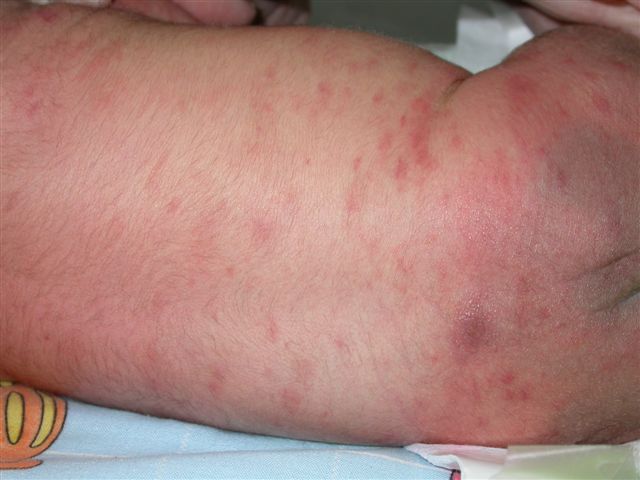
I saw a new born today at the neonatal ward. He is the first child, just delivered today by LSCS for fetal distress. Noted to have generalized erythematous wheals and papules. Some of the wheals and papules appear to form blisters. The mother had no history of any infection during her pregnancy. On examination the child appeared comfortable and not in distress. Sleeping and quiet. Afebrile. Generalised erythematous raised papules and wheals were noted on the face, trunk and upper limbs. Some of the wheals blanche with pressure. Tried to elicit darier’s sign – mild erythema but not raised. The wheals were intensely erythematous and inflamed on certain parts of the neck and face.

Clinically he has urticaria pigmentosa

His blood counts : TWBC 3100 Eosinophils 20% 
Platelets 44 000
G6PD - pending

Though the rash appeared intense, the child was comfortable. Would you have started him on oral hydroxizine? Would you investigate further – hematological malignancy, etc the parents were advised about trigger factors (rubbing) and drugs (anesthetics, etc). thanks, Henry Foong