This is default featured slide 1 title

Go to Blogger edit html and find these sentences.Now replace these sentences with your own descriptions.

This is default featured slide 2 title

Go to Blogger edit html and find these sentences.Now replace these sentences with your own descriptions.

This is default featured slide 3 title

Go to Blogger edit html and find these sentences.Now replace these sentences with your own descriptions.

This is default featured slide 4 title

Go to Blogger edit html and find these sentences.Now replace these sentences with your own descriptions.

This is default featured slide 5 title

Go to Blogger edit html and find these sentences.Now replace these sentences with your own descriptions.

Wednesday, July 19, 2006

Hypopigmentation in atopic dermatitis

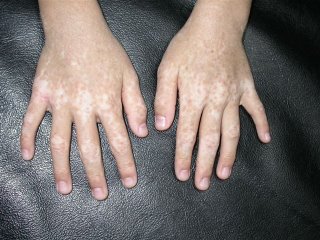
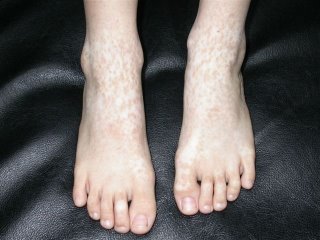
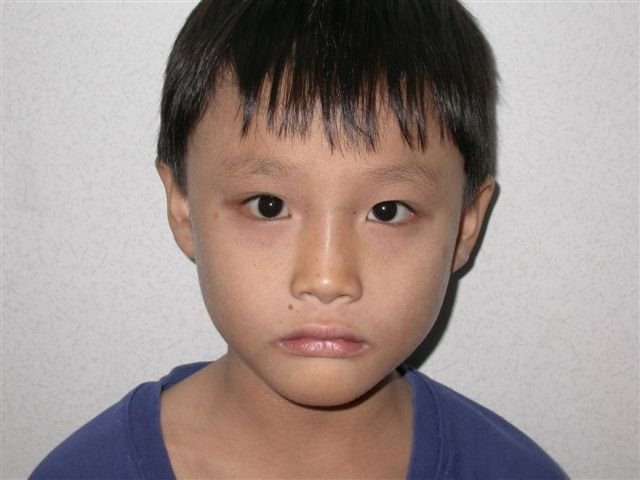
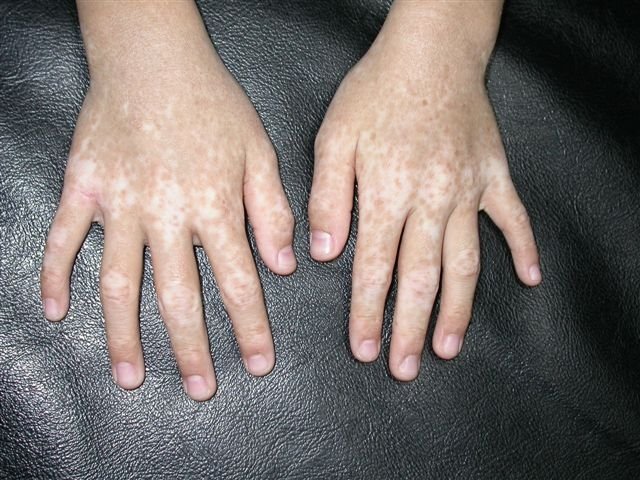
This is a 7-year-old boy who developed multiple patches of hypopigmentation on the dorsum of the hands for 3 years. He had a history of atopic dermatitis and had severe eczema of the hands prior to development of the hypopigmentation on the hands. According to the mother, he had secondary infection with crusts formation on the hands. The lesions were patchy hypopigmented macules mainly on the dorsum of the hands and feet. There were no family history of similar pigmentation. Wood's lamp examination however showed accentuation of the hypopigmented lesions.

Based on history this is most likely post inflammatory. Other differential considered includes vitiligo. Vitiligo is probably unlikely in this patient as the hypopigmentation developed after he had eczema with secondary infection of the hands and feet.

Any suggestions for this hypopigmentation? Would UVB or tacrolimus ointment help?

Thanks for your comments.


Wednesday, July 12, 2006

A Case from New Brunswick

A friend from coastal New Brunswick sent this interesting case:

Dear Dr. Elpern,

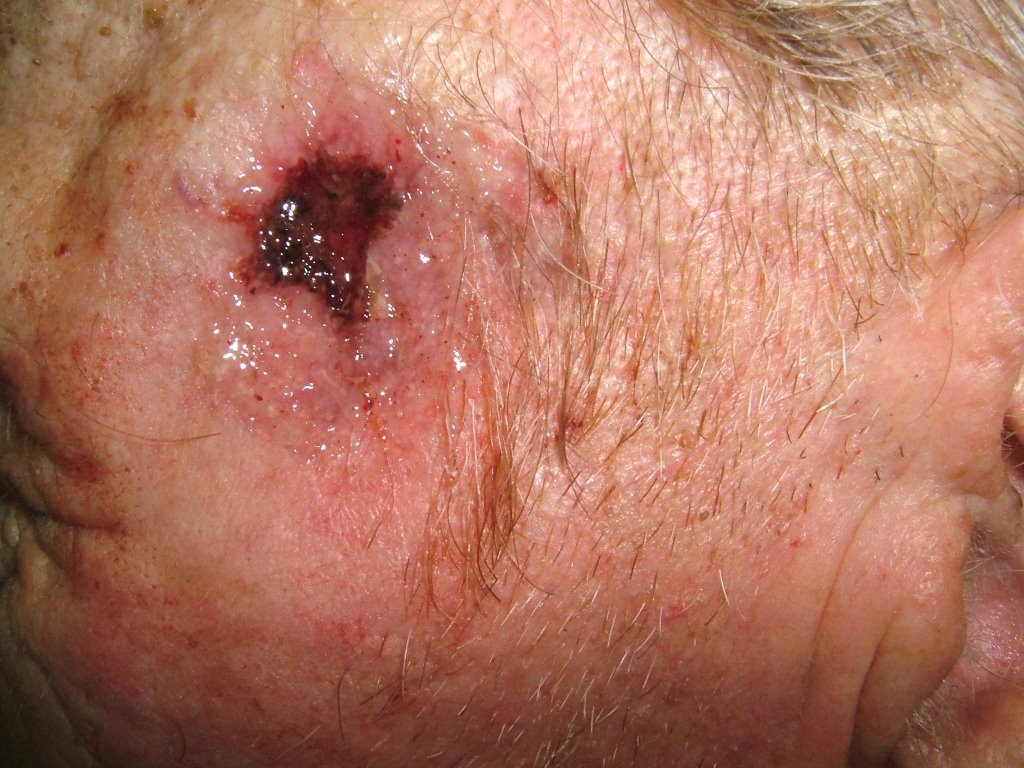
The patient is a 91 year-old working lobsterman who was sent in by his GP for evaluation of a large fungating tumour on his left temple. By history, the lesion has been present for 15 years but has only really increased in size in the past 18 months. He's in vigourous good health otherwise.
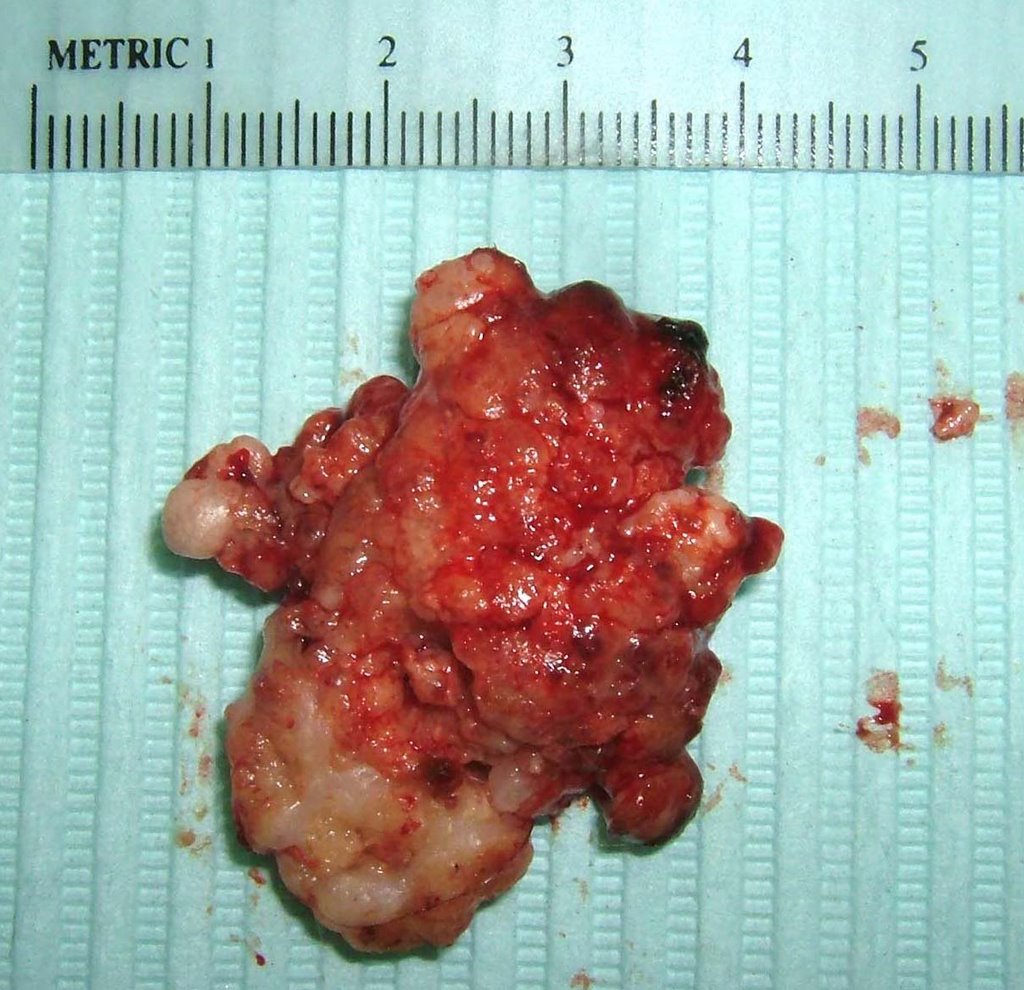
On close examination, the tumour was found to be on a stalk. It's surface measured around 5 cm in diameter, whilst the pedicle was 9 mm in diameter.
After cleaning the area, I administered local anesthesia with lidocaine and epinephrine and snipped it off. I dissicated the base and applied a dressing.
I may follow-up with imiquimod (as recommended by a dermatologic friend) or may excise the defect secondarily.
We occasionally see dramatic tumours like this is watermen. They are a stoic lot.

I wonder, do your colleagues have any suggestions? I will post the path report when it is ready.

Cheers,

Dr. Hamish Dunwoodie, FRCSC
General Surgeon
Moncton, NB, Canada


Thursday, July 6, 2006

Probably Lyme

The patient is a 56 year old man in good general health.
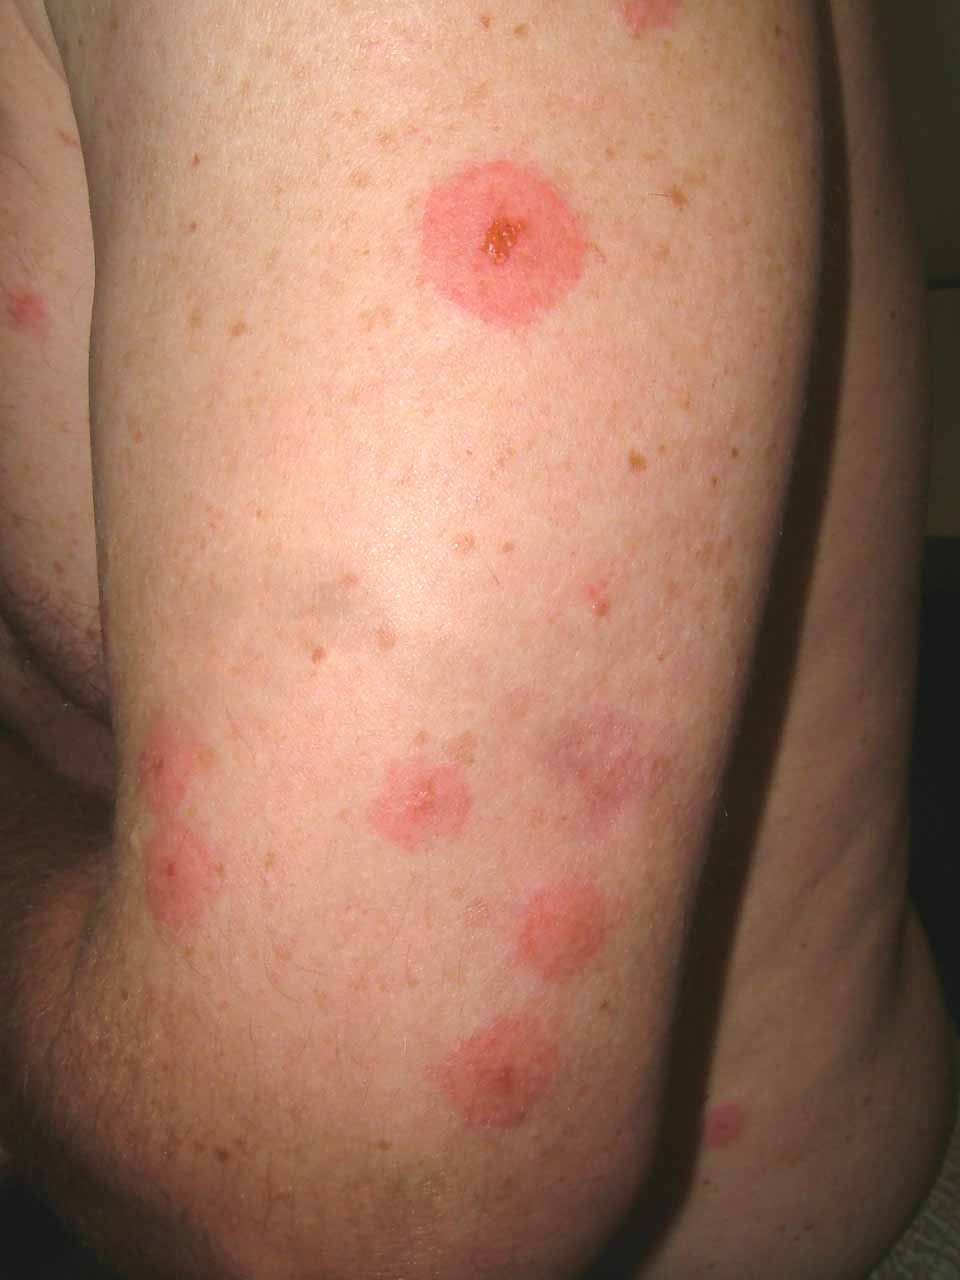
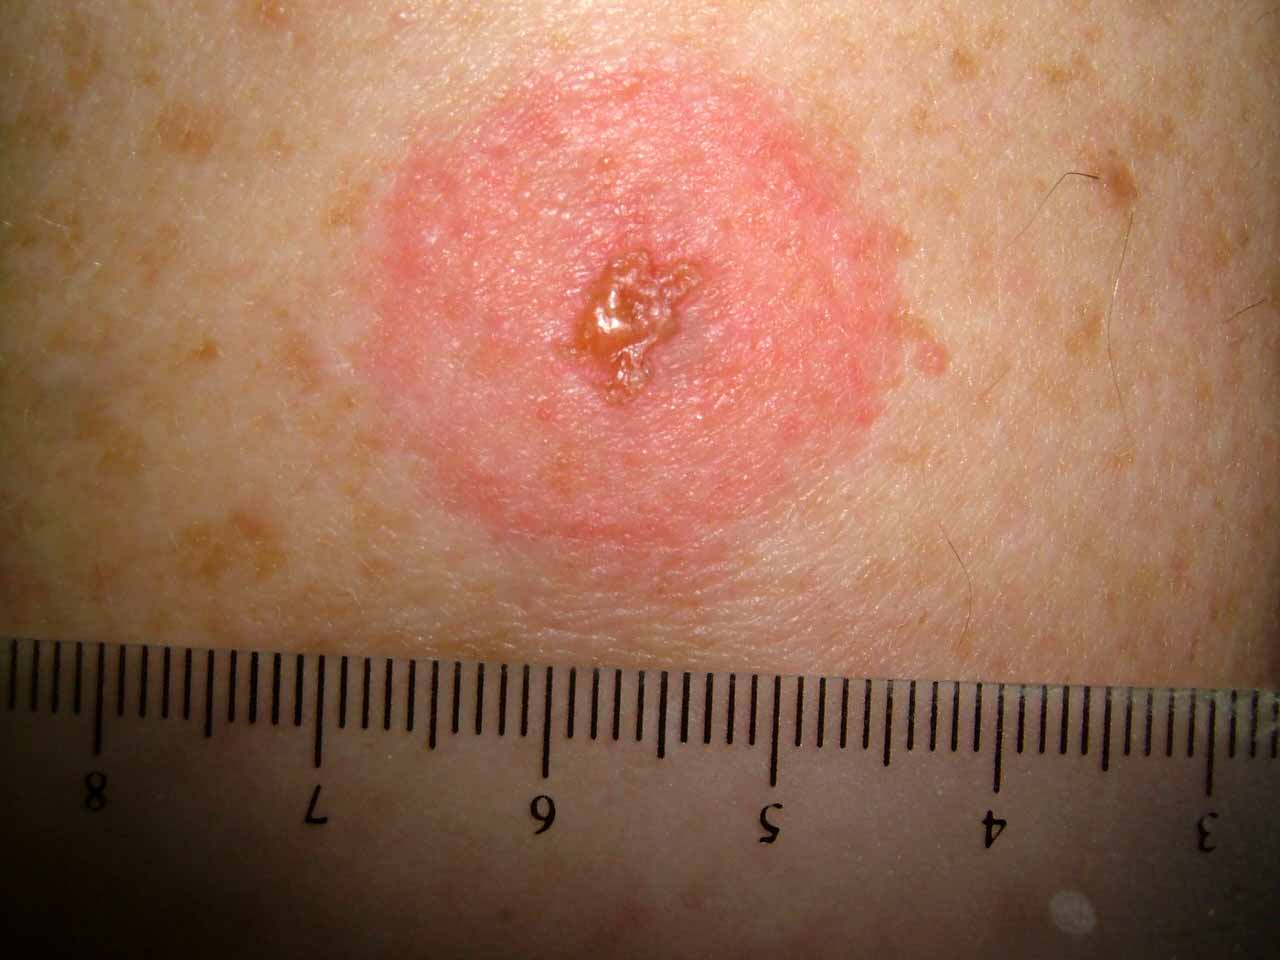
Six days ago, he developed an erythematous papule on the left abdomen.
Over the past week, this has grown into an oval 10 centimeter pruritic erythematous plaque.
This is a solitary lesion and the remainder of the cutaneous exam is unremarkable.
There is no history of tick bite, but this is an endemic area and the patient has an outdoor life-style.

I suspect this is Lyme Disease and that it is too early for serology to be helpful.
After discussion with the patient, he was started on doxycycline 100 mg bid.

(For interest, please see case of June 20th)


Wednesday, June 28, 2006

Eye Lash Alopecia

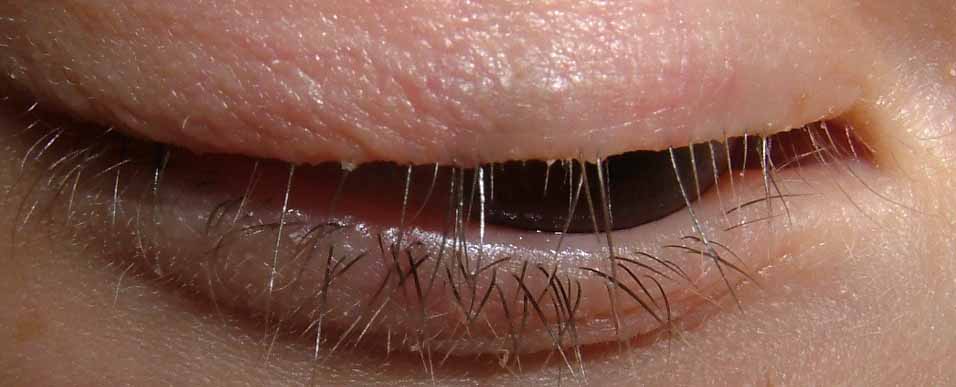
The patient is an eight year old girl who has had a dermatitis of her eyelid margins off an on for around a year. She gets crusted areas which itch and her mother feels she plucks her eyelashes. On the day of the visit the lids looked quiet, but there was definite loss of some eyelashes. There is some evidence of broken lashes.

Question:
Is this eyelash trichotillomania or isolated alopecia areata of the eyelashes? I favor trichotillomania
What is the prognosis for spontaneous recovery?

My plan is to see her if and when the dermatitis is more acute and obtain a culture to see if she has a bacterial blepharitis.


Saturday, June 24, 2006

Bed Bugs

This 35 year-old man went to Mamaronek, New York to watch the New York Open Golf Championship last weekend. The closest motel room he could find was in Bridgeport, Connecticut. The latter is a city with a fairly poor reputation. Two days after returning home to Massachusetts he developed the lesions pictured here on arms and to a lesser extend on torso and legs.

They are consistent with bedbug bites (Cimex lenticularis). For a brief description go to: http://www.emedicine.com/derm/topic600.htm

In November of 2005 a bedbug epidemic was reported in New York in the New York Times. I saw a couple of cases from there here in Williamstown, MA, 150 miles away. I suppose there's a similar problem in Bridgeport now.


Tuesday, June 20, 2006

Lyme Disease

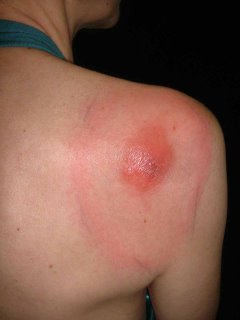
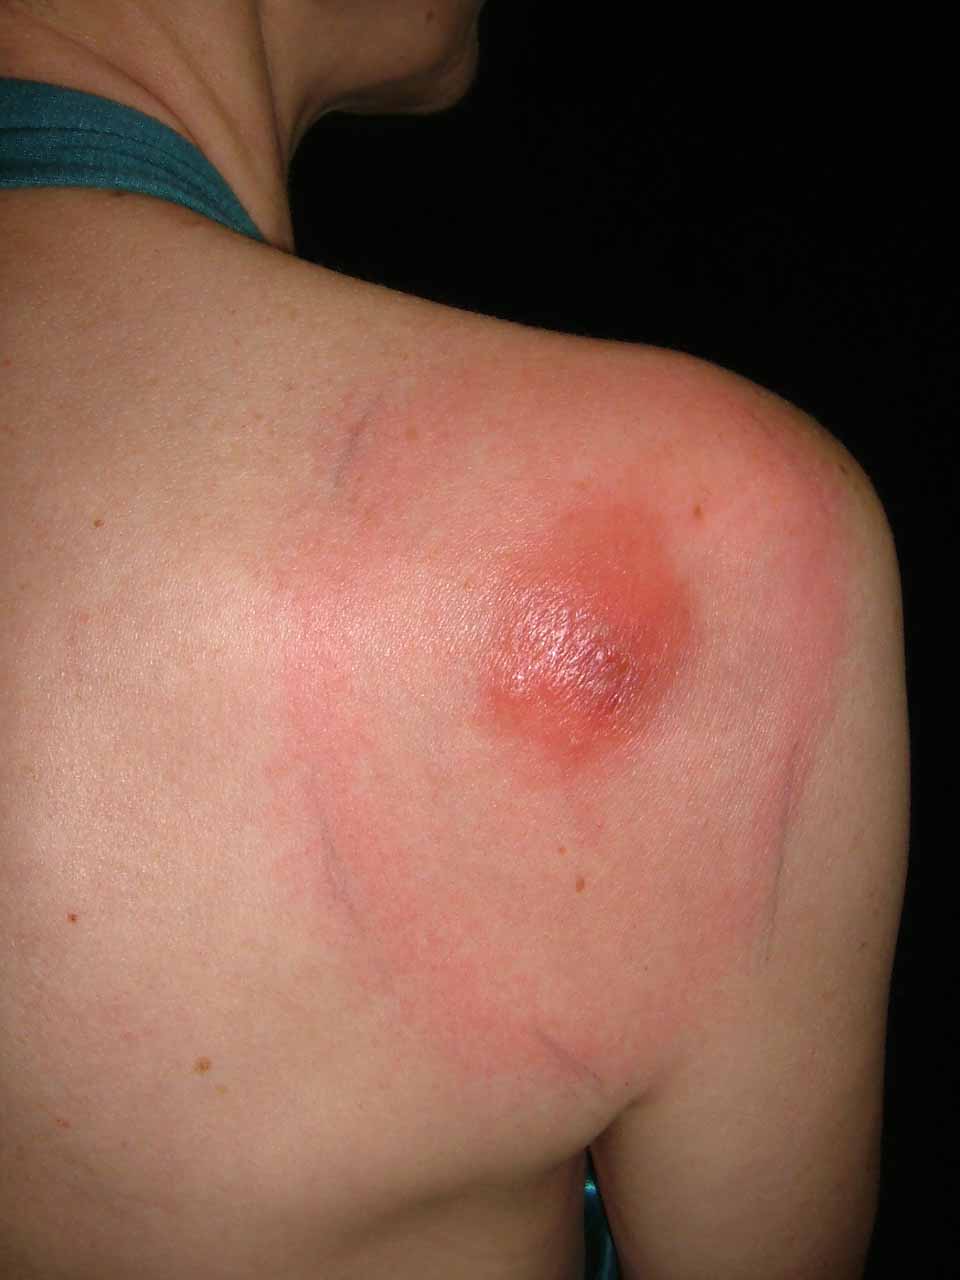
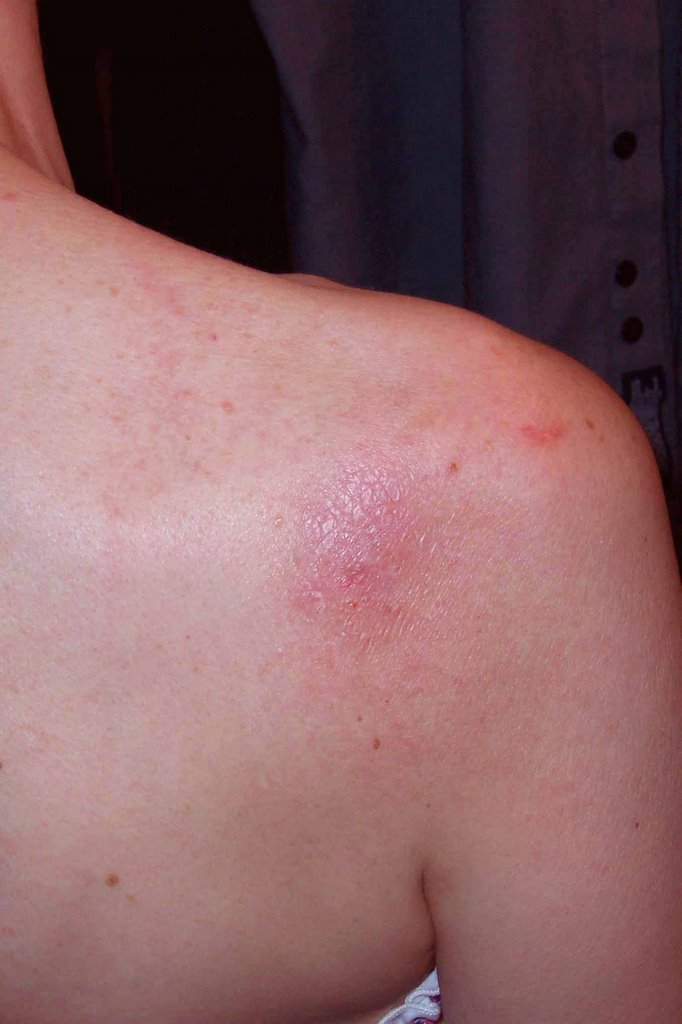
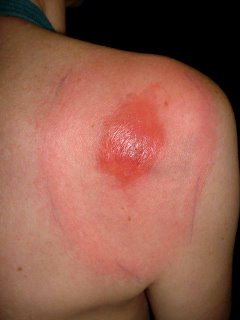
This 52 year-old woman presented as a walk-in patient today. She has a five day history of an erythematous nodule on the right shoulder which has developed a ring around it. The ring measures 9 by 11 centimeters in diameter. Initially, the nodule was painful for a few days; but the pain has subsided. She has had no fever or constutional symptoms and has continued to work as a school teacher.

The patient lives in rural New Hampshire and gardens a fair bit. She was seen two times at a primary care clinic where a diagnosis of spider bite was made. First she was given Keflex, then amoxicillin.

Diagnosis: I am uncertain. I favor Lyme Disease but this has atypical features. The central nodule is unusual, although the peripheral ring looks like Lyme. I also considered atypical Sweet's Disease and a pyogenic process. Lastly, I thought of eosinophilic cellulitis (Well's Syndrome) which I have never seen.

Plan: Since she feels well, I prescribed Doxycycline 100 mg bid, and ordered a cbc, Lyme titers and a G6PD (if the lesion becomes necrotic may want to try Dapsone. I considered biopsy but was strapped for time and thought Lyme most likely. Now, I am uncertain. Biopsy will be done when she is seen in follow-up unless she is significantly better.

Your thoughts will be welcome.


Addendum:

Path Report:
DIAGNOSIS: Skin - (A) Right Shoulder-Periphery-Ring Surrounding Nodule:
Tight, mild superficial and deep perivascular lymphocytic infiltrate .
NOTE : These changes are those of a dermal hypersensitivity reaction to an exogenous antigen and, given the clinical presentation, are consistent with erythema chronicum migrans .

DIAGNOSIS: Skin - (B) Right Shoulder-Nodule:
Broad scale crust containing neutrophils , epidermal hyperplasia , marked papillary dermal edema and a superficial and deep perivascular and interstitial mixed inflammatory cell infiltrate composed of lymphocytes , neutrophils , histiocytes and plasma cells with rare eosinophils consistent with arthropod bite reactio n.
NOTE : These changes may be seen in a tick bite and erythema chronicum migrans . Clinico-pathologic correlation is suggested.

The Lyme Titer is positive.

In my opinion, this is not definitive, but the onus is on me at this time to continue to treat for Lyme.
The patient is on doxycycline and will continue on this at a dose of 100 mg bid for three weeks.
The patient reports that after three days of doxycycline the lesion is smaller. This, too, is not definitive, however, one can not ignore that either.


One Week Follow-up.
The patient feels better. Has mild insomnia.
Although initial lab titer was positive -- the Western Blot was negative indicating an early infection. Our infectious disease consultant expected them to be negative. Early treatment can prevent conversion. Will probably repeat in 2 weeks.

Picture on June 29, 2006
Wednesday, June 7, 2006

Erosio interdigitalis blastomycetica


Why do dermatologists love these cumbersome terms??

The patient is a 30 yo woman with a two week history of a sore area between the 3rd and 4th toes of the left foot. She is in good general health. Not pregnant and on no oral contraceptives. Both parents have Type II diabetes. At the time of onset she was on doxycycline for rosacea.

The examination shows an erosion in the toe web. The KOH prep was positive for pseudohyphae consistent with the diagnosis of erosio interdigitalis blastomycetica

Given her family history she should be worked up for diabetes. The doxycycline may have also played a role.

The role of maceration was discussed. She will keep toes separated and use ketoconazole cream. If this in not effective, I will ask her to dry area after bathing with a hair dryer and continue an imidazole cream or solution.

This is from emedicine.com:
Intertrigo: Intertrigo typically presents with erythema, cracking, and maceration with soreness and pruritic symptoms. Lesions typically have an irregular margin with surrounding satellite papules and pustules. Web spaces of affected fingers or toes are macerated and have the appearance of soft white skin, which is a condition termed erosio interdigitalis blastomycetica (interdigital candidosis).

A good source for the treatment of intertrigo is at: http://www.emedicine.com/derm/topic198.htm